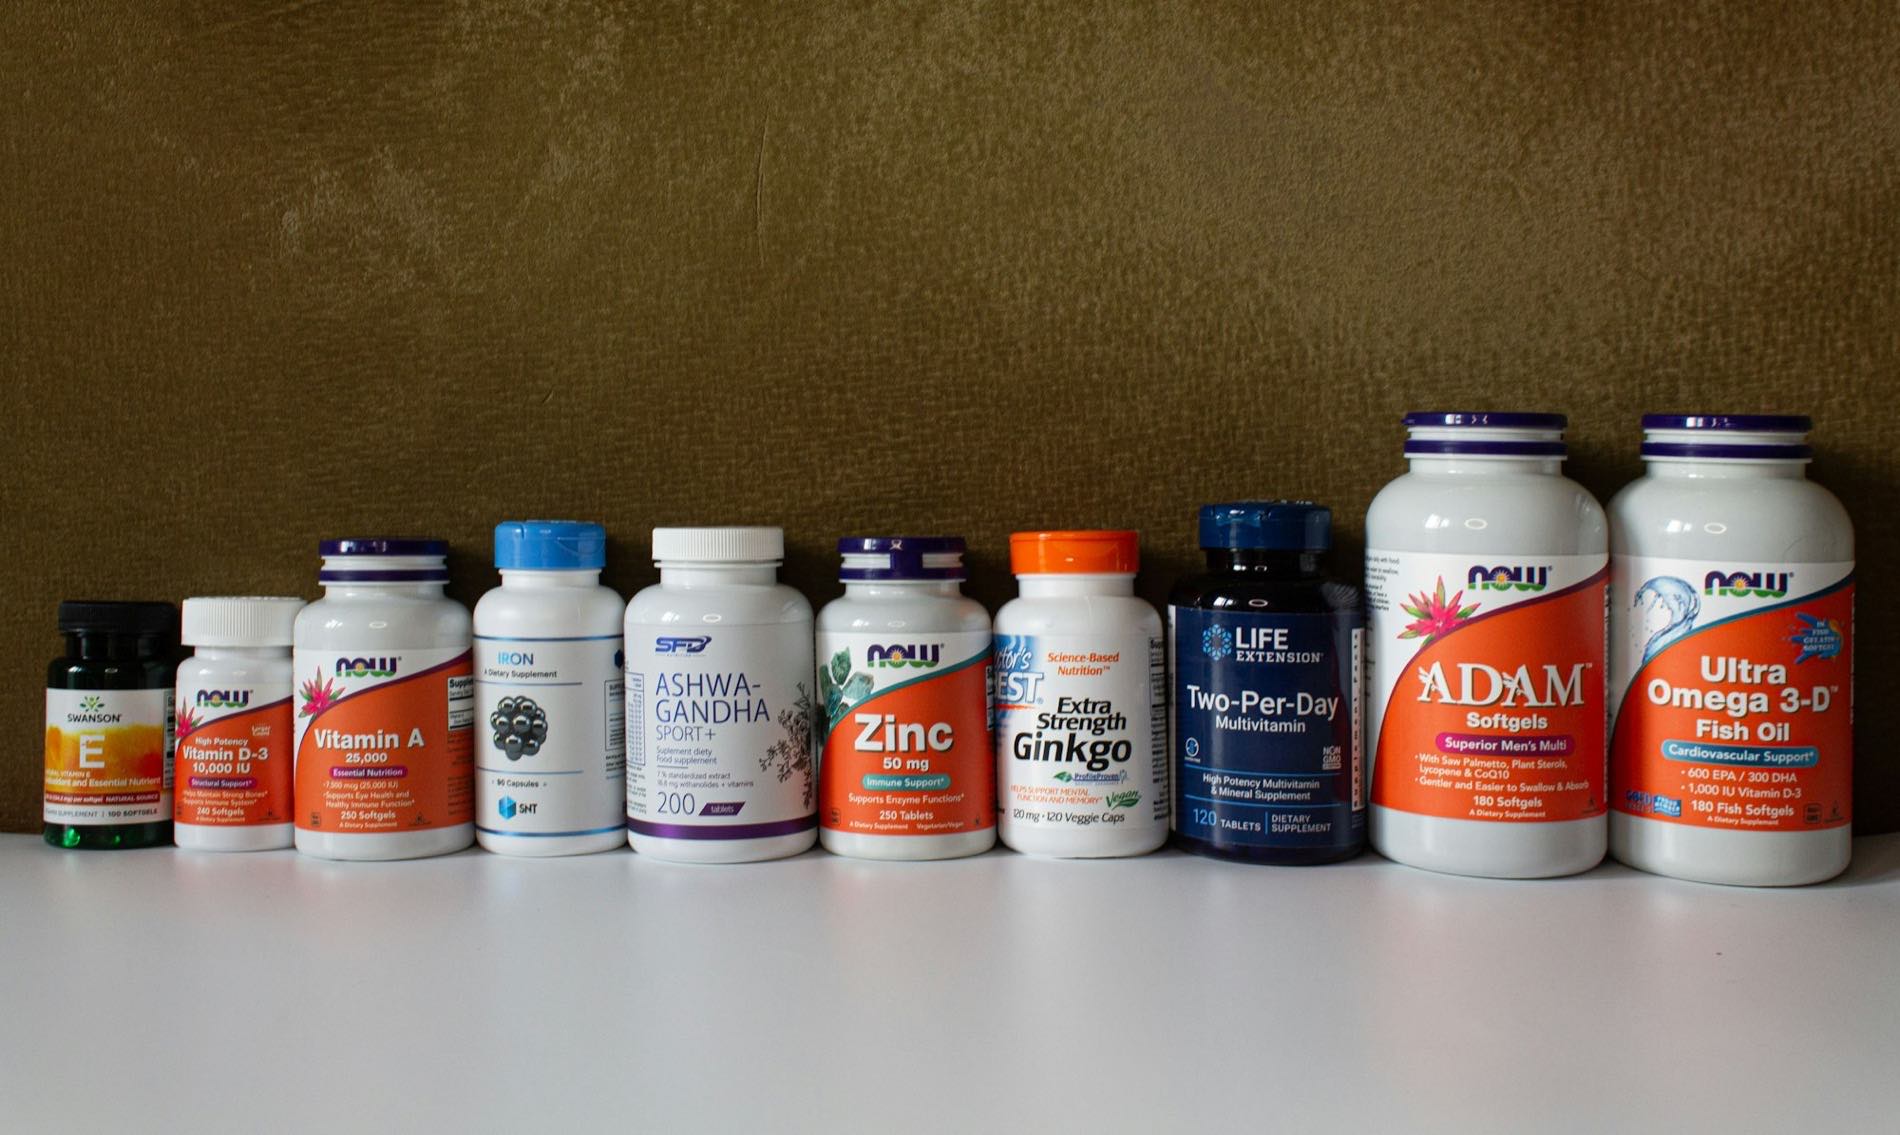
Feeling tired all the time despite getting enough sleep? Micronutrient deficiencies are often the overlooked culprit — and standard lab panels are specifically designed to miss them until deficiency becomes severe.
Why You Can Be Well-Fed and Still Deficient
The modern food supply is calorie-dense and micronutrient-poor. Highly processed foods — which now make up more than half of the average American's caloric intake — have been stripped of the vitamins, minerals, and phytonutrients that whole foods naturally contain. Even people who eat relatively well can fall short of optimal micronutrient status due to soil depletion, food processing, cooking losses, and the increased demands that chronic stress, medications, and gut dysfunction place on the body's nutrient reserves.
This is not a fringe concern. The National Health and Nutrition Examination Survey consistently finds that a significant proportion of the U.S. population fails to meet the Estimated Average Requirement for magnesium, vitamin D, vitamin E, calcium, and several B vitamins. And the Estimated Average Requirement is a floor — the minimum needed to prevent deficiency disease — not the optimal level for energy, cognitive function, and long-term health.
The Mitochondrial Connection
To understand why micronutrient deficiencies cause fatigue, you need to understand how the body produces energy. Every cell in the body generates energy through a process called oxidative phosphorylation, which takes place in the mitochondria. This process requires a continuous supply of specific micronutrients as cofactors — B vitamins (B1, B2, B3, B5), magnesium, coenzyme Q10, iron, and others. Without adequate levels of these cofactors, the mitochondria cannot produce ATP efficiently, and fatigue is the inevitable result.
This is why fatigue is one of the earliest and most consistent symptoms of micronutrient deficiency — and why it often persists even when sleep is adequate and thyroid function appears normal. The machinery of energy production is simply not running at full capacity. Addressing the deficiencies does not just reduce fatigue — it restores the fundamental cellular process that underlies every aspect of physical and cognitive performance.
The Most Common Deficiencies Behind Chronic Fatigue
In clinical practice, certain micronutrient deficiencies appear repeatedly in people presenting with chronic fatigue. The table below outlines the most common, their associated symptoms, and important nuances in how they are best assessed.
| Nutrient | Key Symptoms | Clinical Note |
|---|---|---|
| Iron / Ferritin | Fatigue, cold intolerance, hair loss, poor concentration | Ferritin below 50 ng/mL is often symptomatic even when hemoglobin is normal |
| Vitamin B12 | Fatigue, brain fog, mood instability, peripheral tingling | Serum B12 can appear normal while functional deficiency exists — methylmalonic acid is a more sensitive marker |
| Vitamin D | Fatigue, low mood, immune dysfunction, muscle weakness | Optimal range is 50–80 ng/mL; most conventional labs flag deficiency only below 20 |
| Magnesium | Fatigue, insomnia, anxiety, muscle cramps, headaches | Serum magnesium is a poor indicator — RBC magnesium or intracellular testing is more accurate |
| Zinc | Fatigue, poor wound healing, immune dysfunction, hair thinning | Depleted by stress, high sugar intake, and many medications |
| CoQ10 | Fatigue, exercise intolerance, brain fog | Depleted by statin medications; critical for mitochondrial energy production |
| B-Complex (B1, B2, B3, B6, Folate) | Fatigue, mood instability, poor stress resilience, neuropathy | B vitamins are cofactors for hundreds of enzymatic reactions including energy metabolism and neurotransmitter synthesis |
Why Standard Lab Panels Miss These Deficiencies
The reference ranges used in standard blood panels are designed to identify frank deficiency — the level at which clinical disease becomes apparent. They are not designed to identify the subclinical insufficiency that impairs energy, mood, and cognitive function without producing a diagnosable condition. A serum magnesium level, for example, can appear normal even when intracellular magnesium is significantly depleted, because the body tightly regulates serum levels at the expense of tissue stores. A vitamin D level of 22 ng/mL will not be flagged as deficient on most standard panels, but the research literature consistently shows that levels below 40–50 ng/mL are associated with fatigue, immune dysfunction, and mood disturbance.
Functional micronutrient testing — such as SpectraCell's Micronutrient Panel — measures nutrient status inside the cell over a 4–6 month period, providing a much more accurate picture of functional sufficiency than a single serum measurement. This distinction matters enormously in clinical practice, because it reveals deficiencies that standard panels consistently miss.
Addressing Deficiencies: More Than Just Supplementing
Identifying a micronutrient deficiency is the beginning of the work, not the end. The next question is always: why is this deficiency present? In some cases, the answer is straightforward — inadequate dietary intake. But in many cases, the deficiency reflects a deeper issue: poor gut absorption, chronic stress depleting reserves faster than they can be replenished, medications blocking absorption or increasing excretion, or genetic variants affecting how nutrients are metabolized.
A person with an MTHFR variant, for example, may have difficulty converting folic acid to its active form, methylfolate — and supplementing with the wrong form of folate will not resolve the deficiency. A person with low stomach acid due to long-term proton pump inhibitor use will not absorb B12 adequately regardless of how much they consume. A person with untreated celiac disease or non-celiac gluten sensitivity may have impaired absorption of iron, zinc, and fat-soluble vitamins across the board.
Functional nutrition addresses these root causes alongside the deficiencies themselves. The goal is not just to normalize a lab value — it is to restore the conditions under which the body can maintain adequate nutrient status on its own.
Never Miss a Wellness Insight
New articles on functional nutrition, integrative wellness, and root-cause health — delivered straight to your inbox. No fluff, no spam.
We respect your privacy. Unsubscribe at any time.

Written by
Julia Callaghan, CLT
Julia is a Functional Nutritionist and Certified LEAP Therapist based in Charlotte, NC. She specializes in functional lab testing, root-cause nutrition, and personalized micronutrient protocols that address the underlying drivers of fatigue, mood instability, and chronic symptoms.